


Power of Ideas
SHARE

SHARE
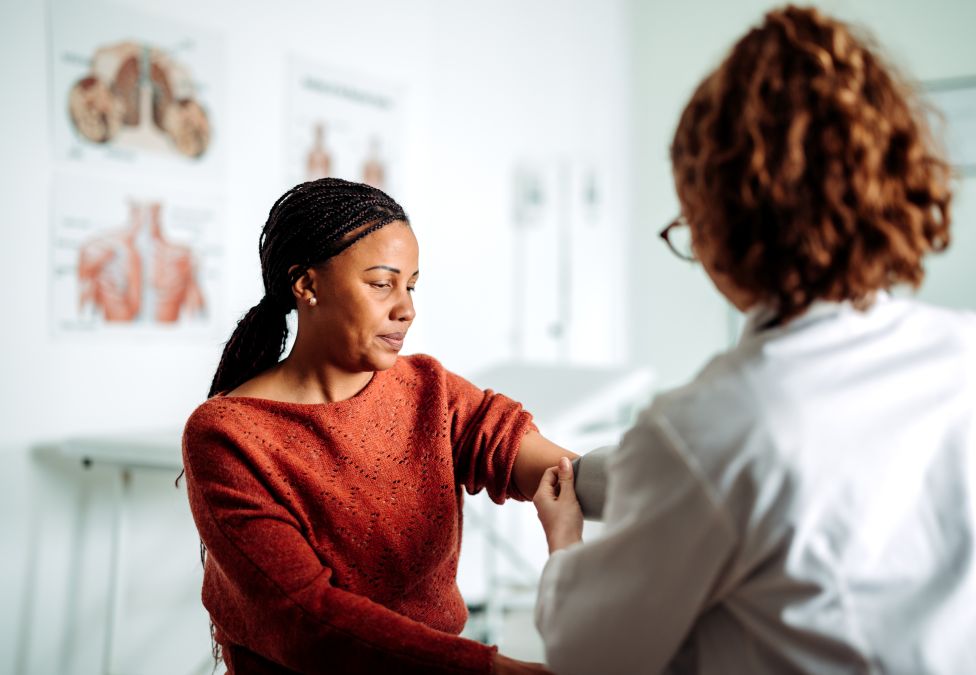
When we talk about making better health accessible to more people, we usually mean better doctors, better diagnostics, and better treatments. But access to better health must also mean access to prevention: the opportunity to protect our health before disease takes hold.
Nowhere is that opportunity more overlooked than in women’s brain health.
We need to move prevention upstream—and build the infrastructure to make it part of everyday health care.
Ask women what they fear most about aging, and many will tell you it is losing their memory, if not their sense of self. Yet a woman can spend decades conscientiously undergoing mammograms, Pap tests, colonoscopies, cholesterol checks, and bone-density scans without anyone ever asking about the health of the organ she may fear losing most: her brain.
Women account for nearly two-thirds of Americans living with Alzheimer’s disease, the most common cause of dementia, according to the Alzheimer’s Association. A woman’s lifetime risk of developing Alzheimer’s is twice as high as a man’s, starting at age 45. Yet conversations about brain health and prevention remain strikingly absent from routine women’s health care.
That omission matters particularly in midlife. Alzheimer’s does not begin when memory fails. The biological changes underlying the disease can develop years, even decades, before symptoms appear. Meanwhile, important contributors to dementia risk—including high blood pressure, high cholesterol, diabetes, physical inactivity, and depression—can emerge or intensify during midlife, and many are modifiable. We have an opportunity to act long before cognitive impairment develops.
For women, midlife also brings menopause, a major neuroendocrine (brain-hormone) transition impacting far more than fertility. While traditionally associated with the ovaries, menopause impacts the brain as well as the reproductive system. Hot flashes themselves originate in the brain, and many women report changes in memory, concentration, sleep, and mood. These symptoms deserve clinical attention in their own right, while research continues to clarify how reproductive aging may influence long-term Alzheimer’s risk.
But we do not need to wait for that answer to recognize midlife as an opportunity to protect brain health. If disease develops over decades, prevention cannot begin at its endpoint.
Yet the care women receive rarely connects the dots. Primary care, gynecology, menopause medicine, neurology, and psychiatry too often operate in separate clinical worlds. Our health-care system is organized around organs, specialties, and diseases rather than health across a lifetime. Women should not have to navigate those silos themselves.
The problem goes beyond fragmented care. We have built systems to treat disease, but not necessarily to prevent it. Brain-health prevention is rarely incorporated into routine clinical practice, and access to specialized preventive services is often limited by cost, availability, and inadequate insurance coverage.
We need to move prevention upstream—and build the infrastructure to make it part of everyday health care.
This does not mean screening every middle-aged woman for Alzheimer's disease, nor does it mean treating menopause across the board, or suggesting that dementia can always be prevented. It means making brain-health promotion part of every woman's preventive health toolkit. It means routinely addressing factors that matter for long-term brain health, while developing better ways to identify who is at risk, when intervention is most effective, and which approaches work for whom.
But scientific discovery alone will not create access. Prevention requires more than advising women to eat well, exercise, and see their doctors. Researchers need to generate the evidence, clinicians need up-to-date training and practical tools, health systems should coordinate preventive care across specialties, and insurers should cover evidence-based services. Community and workplace programs also have a role to play in helping women understand their risks and connect with appropriate care.
At the same time, prevention cannot become another advantage reserved for those with the resources, education, or proximity to specialized medical centers to seek it out. If we learn to identify risks earlier but fail to make that knowledge useful to more women, scientific progress could deepen existing inequalities rather than reduce them.
We know a different approach is possible. Cardiovascular medicine changed when we stopped waiting for a heart attack before acting. Blood pressure checks, cholesterol management, smoking cessation, and exercise counseling became part of routine preventive care. Women’s brain health deserves the same transformation.
If we want better health to reach more people, we cannot simply make the end of the health-care journey more accessible. We have to move the starting line. For women’s brain health, midlife is the frontline of prevention.
SHARE
Related Content
-

Age Is Not a Diagnosis
My father was 73 when doctors started explaining away his abdominal pain. First pancreatitis, then inflamed mesentery.Read Essay -
Before Treating Dementia, We Have to See It
Every three seconds, someone in the world develops dementia.Read Essay -
The Future of Aging and Longevity: A Decade of Progress, A Decade to Act
What will it take to make longer lives better lives for everyone?Read Report -

Mind the Gap: Investing in Dementia as an Opportunity to Extend Healthspan
We are living through an age of remarkable longevity. Globally, the number of people aged 60 and over is projected to double in the next 25 years. But this longevity boom masks a critical problem: the growing gap between lifespan and...Read Report
 CP
-

Improving Early Detection of Cognitive Impairment and Dementia
The prevalence of mild cognitive impairment (MCI) and dementia is increasing as advancements in medicine, public health, and living standards extend human lifespans. Approximately 12–18 percent of Americans aged 60 and older have MCI, and...Read Report
SM
KP
-

Kissick Family Foundation, Milken Institute Announce $3 Million in Funding for Frontotemporal Dementia Research
September 25, 2024 (Washington, DC)—The Kissick Family Foundation Frontotemporal Dementia (FTD) Grant Program, in partnership with the Milken Institute Science Philanthropy Accelerator for Research and Collaboration (SPARC), today announced...Read Article -
Inaugural Kissick Family Foundation FTD Grant Program Awardees and Projects
The Kissick Family Foundation Frontotemporal Dementia (FTD) Grant Program and the Milken Institute Science Philanthropy Accelerator for Research and Collaboration (SPARC) are pleased to announce that six research teams have been awarded...Read Article -
Request for Proposals: Kissick Family Foundation Frontotemporal Dementia Grant Program
2024 Funding Announcement: The Kissick Family Foundation Frontotemporal Dementia (FTD) Grant Program will fund a second cohort of research to understand the fundamental biology of why and how sporadic forms of FTD develop. In partnership...Read Article -

Frontotemporal Dementia Giving Smarter Guide
Frontotemporal dementia (FTD) refers to a family of neurodegenerative conditions that cause changes in behavior, mood, executive function, language, memory, and motor function. FTD is widely believed to be underdiagnosed and undercounted...Read Report

 MM

